





Dr K Narayana Raju

Dr K Narayana Raju

Consultant - Interventional Cardiologist

MBBS, MD, DNB (Cardiology)

20+ years of experience

11,000+ Happy Patients

20+ years of experience

11,000+ Happy Patients

LinQ Card

About Dr K Narayana Raju

Dr. K Narayana Raju is a distinguished Interventional Cardiologist with over two decades of experience in the field of cardiology. He completed his MBBS from M S Ramaiah Medical College, Bangalore, followed by an MD in Internal Medicine from Kasturba Medical College, Mangalore, and DNB in Cardiology from Narayana Hrudayalaya, Bengaluru. Throughout his career, he has been committed to providing cutting-edge cardiac care with a focus on advanced interventions and patient-centric treatment. Known for his meticulous approach and compassionate care, he specializes in managing complex heart conditions, performing minimally invasive procedures, and guiding patients through tailored treatment plans. His extensive expertise, combined with his dedication, makes him a trusted name in cardiology practice.


https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/482085537_1151651480083952_5204855945032068370_n_0.jpg

Dr. K Narayana Raju is renowned for his excellence in interventional cardiology, delivering innovative and effective treatments for various heart diseases. He is committed to achieving the best outcomes through precision and advanced techniques, ensuring patient safety and comfort. His compassionate approach and clear communication build trust and confidence among his patients. With a strong focus on personalized care, Dr. K Narayana Raju strives to improve quality of life for his patients, combining clinical expertise with the latest technology. His dedication to continuous learning and patient well-being makes him a leader in the field of interventional cardiology.


Dr K Narayana Raju 's Areas of expertise

  • Complex Coronary Interventions: Treating difficult coronary artery blockages such as chronic total occlusions, bifurcation lesions, and calcified deposits with advanced techniques like rotablation. 
  • Structural Heart Interventions: Minimally invasive repair and replacement of heart structures, including valve replacements like TAVI, TMVR, and device closures like MitraClip and Tricuspid Repair. 
  • Adult Congenital Heart Disease Management: Care focused on the unique challenges of congenital heart defects in adults, improving heart function and symptom control.
  • Advanced Echocardiography: Using TTE, TEE, and 3D Echo imaging to visualize cardiac anatomy and function in detail for accurate diagnosis.
  • Heart Failure Management: Strategies to improve cardiac output, reduce symptoms, and prevent hospitalizations in patients with weakened heart function.
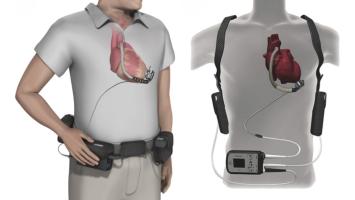
  • Mechanical Circulatory Support: Devices such as intra-aortic balloon pumps assist the heart in maintaining adequate blood flow during critical illness.
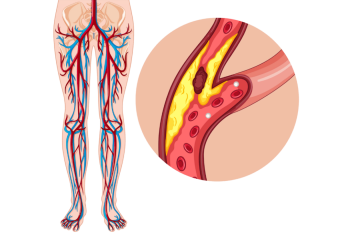
  • Peripheral Vascular Interventions: Treatments aimed at restoring blood flow in peripheral arteries affected by blockages or narrowing.
  • Cardiac Catheterization in Complex Valvular Disease: Catheter-based techniques to diagnose and treat various valvular heart problems, including stenosis and regurgitation.
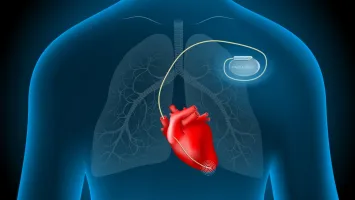
  • Pacemaker & ICD Implantation: Devices that regulate abnormal heart rhythms, preventing dizziness, syncope, and sudden cardiac events.
  • Critical Care & Preventive Cardiology: Emergency cardiovascular stabilization and long-term risk management to prevent heart disease. 


Article:

Article by Dr. K. Narayana Raju on the increasing incidence of heart attacks among young people — their causes, symptoms, and preventive measures.

photo of media

photo of media

An article by Dr. K. Narayana Raju on how habits such as stress, smoking, and alcohol consumption can contribute to high blood pressure. Adopting a healthier lifestyle and monitoring your blood pressure regularly can help keep it under control and support long-term heart health.

No photo description available.

No photo description available.

Publications:  

  • Renal sympathetic denervation using an externally irrigated radiofrequency ablation catheter for the treatment of resistant hypertension - Acute safety and short-term efficacy. Indian Heart Journal. 2015 May-Jun; 67(3):207-213.
  • Renal denervation in a patient with Alport syndrome and rejected renal allograft. Indian Heart Journal. 2015 Dec; 67(Suppl 3): S71–S73. 

Paper Presentation:  

  • Study of the association between HbA1C and acute coronary syndrome in patients with type II diabetes mellitus. 

Clinical Trial Experience:  

  • A descriptive study to correlate left ventricular functions and etiology in left bundle branch block patients.
  • Successful or unsuccessful thrombolysis with streptokinase in acute myocardial infarction: A descriptive study.
  • A prospective study to correlate angiographic profile and clinical outcome of acute coronary syndrome patients with atrial fibrillation.
  • Study of diastolic dysfunction in young (<40 years) newly detected diabetics and its correlation with obesity, glycaemic levels, and dyslipidemia.
  • Cardiac manifestation involvement in dengue infection. 


  • MBBS from M S Ramaiah Medical College, Bengaluru
  • MD in Internal Medicine from Kasturba Medical College, Mangalore
  • DNB in Cardiology from Narayana Hrudayalaya, Bengaluru 

Conditions and Treatments

Complex Coronary Interventions

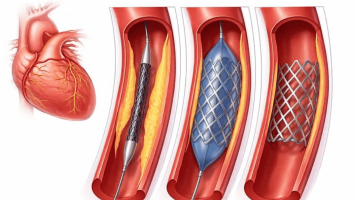
These procedures address severe or difficult coronary artery blockages that standard methods can't resolve, such as chronic total occlusions or bifurcation lesions. Dr. K Narayana Raju’s expertise lies in precisely navigating challenging anatomies and utilizing advanced tools like rotablation, ensuring optimal restore blood flow and reduce the risk of heart attacks. His meticulous analysis helps in selecting the best intervention strategy for each patient, leading to successful outcomes even in complex cases.

Structural Heart Interventions

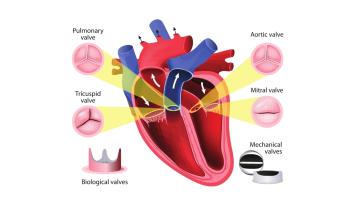
This minimally invasive approach is used to treat structural abnormalities like faulty valves or enlarged heart chambers, often because traditional surgery carries high risks. Dr. K Narayana Raju’s proficiency in TAVI, TMVR, MitraClip, and Tricuspid Repair ensures accurate device placement and successful repair, restoring normal heart function. His careful evaluation of each patient’s anatomy and condition guarantees personalized and effective treatment plans, improving quality of life.

Adult Congenital Heart Disease Management

Adults with congenital heart defects face unique challenges, including arrhythmias and heart failure. Dr. K Narayana Raju’s deep understanding of congenital conditions allows him to develop tailored treatment strategies that optimize heart function and reduce symptoms. His precise assessment helps in planning interventions that are minimally invasive yet highly effective, enhancing long-term health outcomes.

Advanced Echocardiography

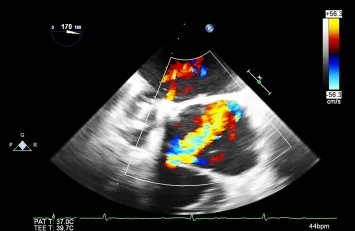
Using TTE, TEE, and 3D Echo, detailed imaging of the heart’s structures and function is achieved, which is crucial for diagnosing complex conditions. Dr. K Narayana Raju’s expertise in interpreting these images allows him to detect subtle abnormalities and plan appropriate interventions. His analytical skill ensures that the imaging results translate into precise, targeted treatment approaches.

Heart Failure Management

Heart failure leads to progressive deterioration of the heart’s pumping ability, requiring comprehensive and carefully tailored strategies to improve symptoms and prevent hospitalization. Dr. K Narayana Raju excels in analyzing the severity and underlying causes, applying the latest evidence-based treatments to stabilize and improve heart function. His holistic approach ensures that each patient’s therapy aligns with their specific condition and needs.

Mechanical Circulatory Support

Devices like intra-aortic balloon pumps are used to support critically ill patients with severe heart failure or cardiogenic shock. Dr. K Narayana Raju’s expertise in deploying and managing these devices ensures adequate tissue perfusion and stabilization. His careful analysis of patient condition guides optimal device use, maximizing benefits and minimizing complications during recovery.

Peripheral Vascular Interventions

Blockages in peripheral arteries can cause limb ischemia and other complications; these are managed through minimally invasive procedures to restore blood flow. Dr. K Narayana Raju’s skills in analyzing vascular anatomy enable him to choose the most effective intervention, reducing symptoms like pain and preventing tissue loss. His precise approach ensures long-lasting results and improved limb function.

Cardiac Catheterization in Complex Valvular Disease

For various valvular problems like stenosis or regurgitation, catheter-based techniques provide less invasive treatment options. Dr. K Narayana Raju’s thorough assessment of valve anatomy and function ensures accurate diagnoses and effective interventions, often avoiding the need for open surgery. His expertise helps in achieving durable valve repair or replacement, improving patient outcomes.

Pacemaker & ICD Implantation

These devices are critical for regulating abnormal heart rhythms and preventing sudden cardiac death. Dr. K Narayana Raju’s skill in analyzing electrical activity and selecting the appropriate device ensures reliable rhythm management. His precise implantation technique results in high success rates and enhances the patient’s quality of life.

Critical Care & Preventive Cardiology

Emergency interventions stabilize acute cardiac conditions, while preventive strategies aim to reduce future risks. Dr. K Narayana Raju’s comprehensive approach combines immediate critical care with lifestyle modifications and risk factor management, helping patients maintain heart health long-term. His detailed analysis and personalized care lead to better recovery and prevention of recurrent cardiac events.

Secondary Prevention After Coronary Artery Disease: Protecting the Treated Heart for the Long Term

Coronary intervention treats the blockage. It does not cure the underlying disease. Atherosclerosis continues in the coronary vessels not treated, and can progress in the treated vessel if the risk factors that drove it are not actively managed. Secondary prevention, the structured long-term management of all modifiable cardiovascular risk factors after a coronary event or coronary intervention, determines whether a patient achieves years of good cardiac health or returns to the catheterisation laboratory with a new event. Dr. K Narayana Raju, DNB Cardiology from Narayana Hrudayalaya, Bengaluru, Consultant Interventional Cardiologist at Hridhay Heart Center, Gajuwaka, Visakhapatnam, with clinical research on the association between HbA1c levels and acute coronary syndrome outcomes in type 2 diabetes, regards secondary prevention as the continuation of cardiac care that begins the moment the procedure ends. The five evidence-based pillars are: smoking cessation, the single most impactful lifestyle intervention, halving the risk of recurrent coronary events within one year of quitting; blood pressure control to below 130 by 80 mmHg, which significantly reduces the mechanical stress on arterial walls and coronary plaques; LDL cholesterol reduction to below 70 mg/dL with high-intensity statin therapy, which stabilises plaques and reduces the burden of new atherosclerotic lesion formation; diabetes control with HbA1c maintained as close to normal as safely achievable, reflecting the specific importance of glycaemic management in the Visakhapatnam population where type 2 diabetes is highly prevalent among coronary patients; and regular physical activity, which reduces cardiovascular mortality, improves heart function, and lowers multiple risk factors simultaneously. Cardiac rehabilitation, a supervised programme of graduated exercise with education and psychological support, reduces cardiovascular mortality by approximately 25 percent in patients who complete it.

Coronary Angiography: The Definitive Roadmap for Coronary Artery Disease Management

Coronary angiography, also called cardiac catheterisation, is the definitive diagnostic procedure for coronary artery disease. It provides the detailed map of the coronary arterial anatomy that is the foundation of every subsequent treatment decision, and in many cases the treatment itself, coronary stenting, is performed at the same sitting through the same access point. The procedure is performed through the radial artery at the wrist: the skin is numbed with local anaesthetic, a small introducer sheath is inserted into the artery, and a thin flexible catheter is advanced from the wrist through the arterial system and positioned at the origin of each coronary artery under real-time X-ray guidance. Iodinated contrast material is then injected through the catheter into each coronary artery, making the vessel visible under X-ray fluoroscopy. The procedure typically takes 30 to 45 minutes, and the patient remains awake throughout, experiencing no pain during the procedure itself. A brief warmth may be felt when the contrast is injected. Dr. K Narayana Raju, DNB Cardiology from Narayana Hrudayalaya, Bengaluru, Consultant Interventional Cardiologist at Hridhay Heart Center, Gajuwaka, Visakhapatnam, performs coronary angiography through radial access and provides a detailed account of the findings to every patient immediately after the procedure. The angiographic images reveal the coronary anatomy in its full detail: which vessels are affected, the precise location of narrowings within each vessel, the percentage luminal diameter reduction (a narrowing of 70 percent or more is generally haemodynamically significant), the length of each lesion, and the morphological characteristics of each lesion including whether it is concentric or eccentric, calcified, involving a bifurcation, or representing a chronic total occlusion of more than three months duration. This information directly determines whether coronary stenting, bypass surgery, or medical management alone is the appropriate next step.

Dr K Narayana Raju 's Expert Tips & Health Insights

Latest

Articles by Dr K Narayana Raju

https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2026-09/Coronary%20Artery%20Disease.png
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/Social%20media%20posters%20%2859%29.jpg
By: Dr K Narayana Raju
03 September 2026

Coronary Artery Disease: A Complete Patient Guide from Diagnosis to Re…

A Consultant Interventional Cardiologist with DNB Cardiology from Narayana Hrudayalaya, Bengaluru, 20 years, and 11,000 patients at Hridhay Heart Center, Gajuwaka, Visakhapatnam, explains coronary artery disease from first principles to recovery: how plaques form in the coronary arteries, the difference between stable angina and a heart attack, what angiography shows, how the decision between stenting and bypass surgery is made, what complex interventions including rotablation and chronic total occlusion techniques involve, what happens after angioplasty, and how secondary prevention and cardiac rehabilitation protect the treated heart.
Read More
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2026-05/Diabetes%20and%20Heart%20Disease%20-%20Dr.%20K%20Narayana%20Raju.jpg
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/Social%20media%20posters%20%2859%29.jpg
By: Dr K Narayana Raju
09 May 2026

Diabetes and Heart Disease: Why Indians With Type 2 Diabetes Are at Hi…

Type 2 diabetes significantly increases the risk of heart disease in Indians, often leading to silent coronary artery damage. Learn the warning signs, prevention tips, and why early diabetes control is crucial for lifelong heart health.
Read More
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/20180418_cover_2.jpg
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/Social%20media%20posters%20%2859%29.jpg
By: Dr K Narayana Raju
09 October 2025

Living with Congenital Heart Disease as an Adult: Challenges and Moder…

As a cardiologist with over two decades of experience, I have had the privilege of caring for many patients who were born with congenital heart defects.
Read More
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/shutterstock_1133276768.jpg
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/Social%20media%20posters%20%2859%29.jpg
By: Dr K Narayana Raju
09 October 2025

Breaking Down Complex Coronary Blockages: When and Why Advanced Interv…

Throughout my years in the field of interventional cardiology, I’ve seen how coronary artery disease can sometimes present as simple blockages, easily treated with basic procedures.
Read More
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/preventive-cardiology.jpg
https://d2vvc091k8tmib.cloudfront.net/s3fs-public/2025-10/Social%20media%20posters%20%2859%29.jpg
By: Dr K Narayana Raju
09 October 2025

The Critical Role of Preventive Cardiology: Building a Heart-Healthy F…

Over the years, I’ve come to realize that the most meaningful victories in cardiology aren’t always about performing complex procedures or saving lives in emergencies. They are often about prevention — stopping heart disease before it starts or worsens.
Read More

Dr K Narayana Raju 's Patient Testimonial Reviews

Leave a Review

Patient Reviews

Dr K Narayana Raju

Leave a Review

Frequently Asked Questions

Frequently Asked Questions

View all

When can I return to work and start driving again after a coronary stent?

The questions about when to return to work and when to drive are among the most practical and most important that patients ask after coronary intervention, and the answers depend on the nature of the procedure performed, the type of work, and whether a heart attack with any muscle injury preceded the intervention. For elective coronary angioplasty and stenting performed for stable angina, where the procedure was planned rather than emergency, and where the heart muscle is not significantly damaged, the recovery is typically straightforward. Most patients are discharged from Hridhay Heart Center the same day or the morning after the procedure. The wrist access site is closed with a compression band that is removed over several hours. Light activity can be resumed promptly: walking, light household tasks, and sitting at a desk are appropriate from the day after discharge. Most patients performing sedentary or desk-based work can return within one to two weeks. Physical work that involves lifting, carrying, or sustained exertion requires a longer recovery and should be discussed individually based on the extent of coronary disease treated and the heart's overall function. Driving: for private use, most patients can resume driving one to two weeks after elective stenting once they are comfortable turning the steering wheel without wrist discomfort and once their symptoms have settled. For commercial vehicle drivers or those whose licence category has specific medical requirements, the regulations differ and the relevant authority must be notified of the cardiac procedure. For patients who have had a heart attack before or alongside the stenting procedure, the recovery timeline is longer and depends substantially on how much heart muscle was affected. A small heart attack with preserved heart function may allow return to light work within two to four weeks. A large heart attack that has reduced the heart's pumping capacity requires a more extended recovery, formal cardiac rehabilitation, and reassessment of function before return to any demanding work. The practical guidance I give every patient at Hridhay Heart Center is to use how you feel at a given activity as your guide, to not push through chest discomfort or breathlessness, and to contact me at any stage if you are unsure whether what you are experiencing is expected or needs assessment.


Written by
Dr. K Narayana Raju, MBBS, MD, DNB Cardiology (Narayana Hrudayalaya, Bengaluru), Consultant Interventional Cardiologist, Hridhay Heart Center, Gajuwaka, Visakhapatnam 530026. Phone: +91 85999 56999. 

What is rotablation and when is it needed for coronary artery disease?

Rotablation, or rotational atherectomy, is a technique used in interventional cardiology to modify coronary plaques that are so heavily calcified that standard balloon inflation cannot adequately expand them. Understanding why this matters requires understanding what calcification does to a coronary plaque. In a heavily calcified lesion, the plaque contains deposits of calcium that give the arterial wall the consistency of eggshell rather than the pliable tissue of a normal artery. When a standard angioplasty balloon is inflated inside such a vessel, the calcium does not yield: the balloon either inflates in the softer non-calcified segments of the plaque, creating an uneven expansion, or cannot be inflated to the pressure required for full expansion at all. The result is an incompletely expanded stent, which sits unevenly in the vessel, is at higher risk of stent thrombosis and restenosis, and does not perform with the effectiveness that a properly expanded drug-eluting stent delivers. Rotablation solves this problem by modifying the calcium before the balloon and stent are delivered. A rotablation system uses a diamond-tipped burr mounted on a drive shaft, spinning at up to 200,000 revolutions per minute, that is advanced over the coronary guidewire to the calcified lesion and passed through it. The diamond-tipped burr ablates the calcium, converting the rigid calcified plaque into a surface that can be adequately dilated by a balloon and fully expanded by a stent. It does not remove all the plaque, but it modifies the calcium structure sufficiently to allow the stent to expand to its full intended diameter and embed evenly in the vessel wall. The clinical significance of this is that many patients who have been told their coronary disease is too calcified to be treated by stenting, and who have therefore been excluded from less invasive treatment, can in fact be treated by PCI with rotablation, restoring blood flow without the need for bypass surgery. At Hridhay Heart Center, Gajuwaka, Visakhapatnam, rotablation is available as part of the complex coronary intervention programme, and patients referred from across Andhra Pradesh with apparently untreatable calcified coronary disease have been successfully treated here without needing to travel to a metropolitan centre.

Related reading: 

Coronary Artery Disease: A Complete Patient Guide from Diagnosis to Recovery
Breaking Down Complex Coronary Blockages: When and Why Advanced Interventions Matter
Diabetes and Heart Disease: Why Indians With Type 2 Diabetes Are at Higher Coronary Risk
The Critical Role of Preventive Cardiology: Building a Heart-Healthy Future


Written by Dr. K Narayana Raju, MBBS, MD, DNB Cardiology (Narayana Hrudayalaya, Bengaluru), Consultant Interventional Cardiologist, Hridhay Heart Center, Gajuwaka, Visakhapatnam 530026. Phone: +91 85999 56999. 

What does coronary angiography involve, and will it be painful?

Coronary angiography is a procedure that patients anticipate with considerable anxiety, and one of the most useful things I can do for a patient who is about to undergo it at Hridhay Heart Center, Gajuwaka, is give them an honest account of what they will experience. The procedure is performed with the patient awake but sedated enough to be relaxed. The access site is the wrist: the skin over the radial artery is numbed with a small injection of local anaesthetic, which produces a brief stinging sensation that is similar to having a blood test. After the skin is numb, the introducer sheath is placed into the artery painlessly. The catheter is then advanced from the wrist through the arterial system to the heart under real-time X-ray guidance. The patient feels none of this: there are no pain receptors inside the blood vessels or the heart, and the catheter's passage from the wrist to the coronary arteries is entirely without sensation. The only sensation during the procedure itself is a brief flush of warmth that occurs when the contrast material is injected into the coronary arteries, which some patients notice and others do not. The procedure from start to finish takes approximately 30 to 45 minutes. After the procedure, the wrist sheath is removed and a small compression band is placed over the access site, which is worn for several hours. Most patients are able to sit up, eat, and drink within an hour of the procedure, and in elective cases many patients are discharged the same day or the morning after. The wrist access route has replaced the groin route as the standard approach because it is substantially more comfortable after the procedure, allows earlier mobilisation, and has a lower risk of access site complications. For the vast majority of patients, coronary angiography at Hridhay Heart Center is far less frightening in reality than the anticipation of it beforehand.

Related reading: 

Coronary Artery Disease: A Complete Patient Guide from Diagnosis to Recovery
Breaking Down Complex Coronary Blockages: When and Why Advanced Interventions Matter
Diabetes and Heart Disease: Why Indians With Type 2 Diabetes Are at Higher Coronary Risk
The Critical Role of Preventive Cardiology: Building a Heart-Healthy Future
Written by Dr. K Narayana Raju, MBBS, MD, DNB Cardiology (Narayana Hrudayalaya, Bengaluru), Consultant Interventional Cardiologist, Hridhay Heart Center, Gajuwaka, Visakhapatnam 530026. Phone: +91 85999 56999.

What risk factors cause coronary artery disease and which ones can I actually change?

Understanding the risk factors for coronary artery disease is the foundation of both preventing it in people who do not yet have it and slowing its progression in those who do. Risk factors divide into those that cannot be changed and those that can. The non-modifiable factors are age, sex (men develop coronary artery disease earlier than women on average, though women's risk rises sharply after menopause), a family history of premature coronary artery disease in a first-degree relative before the age of 55 in men or 65 in women, and prior coronary events. These factors cannot be changed, but they tell us who needs the most aggressive management of the modifiable factors. The modifiable factors are where the clinical opportunity lies. High LDL cholesterol drives the atherosclerotic process directly: LDL particles penetrate the arterial wall, oxidise, trigger inflammation, and accumulate as plaque. Reducing LDL with high-intensity statin therapy is the most evidence-supported pharmacological intervention in coronary artery disease. High blood pressure exerts continuous mechanical stress on the arterial endothelium, accelerating the sites of endothelial injury at which plaque formation begins: controlling blood pressure to below 130 by 80 mmHg significantly reduces cardiovascular risk. Type 2 diabetes accelerates atherosclerosis through multiple mechanisms and in my clinical research on patients presenting with acute coronary syndrome at Hridhay Heart Center, Gajuwaka, Visakhapatnam, I have specifically studied the relationship between HbA1c levels and coronary event outcomes: the Visakhapatnam population has a very high prevalence of type 2 diabetes, and silent coronary disease in this group is a consistent clinical challenge. Smoking is the most powerful single modifiable risk factor: its cessation produces a 50 percent reduction in recurrent coronary event risk within one year. Physical inactivity, obesity, and chronic psychological stress all contribute and all respond to lifestyle intervention. The most important clinical message is that modifiable risk factors compound each other: a patient who has elevated LDL, high blood pressure, diabetes, and smokes does not have four separate risks but a multiplicatively higher risk than any individual factor alone, and addressing all of them is what determines long-term cardiac health.

Written by Dr. K Narayana Raju, MBBS, MD, DNB Cardiology (Narayana Hrudayalaya, Bengaluru), Consultant Interventional Cardiologist, Hridhay Heart Center, Gajuwaka, Visakhapatnam 530026. Phone: +91 85999 56999. 

Link copied to clipboard!

Reach Dr K Narayana Raju

Hridhay Heart Center

Beside Eaters stop Restaurant, Opp. Chinagantyada Bus stop, Gajuwaka, Visakhapatnam