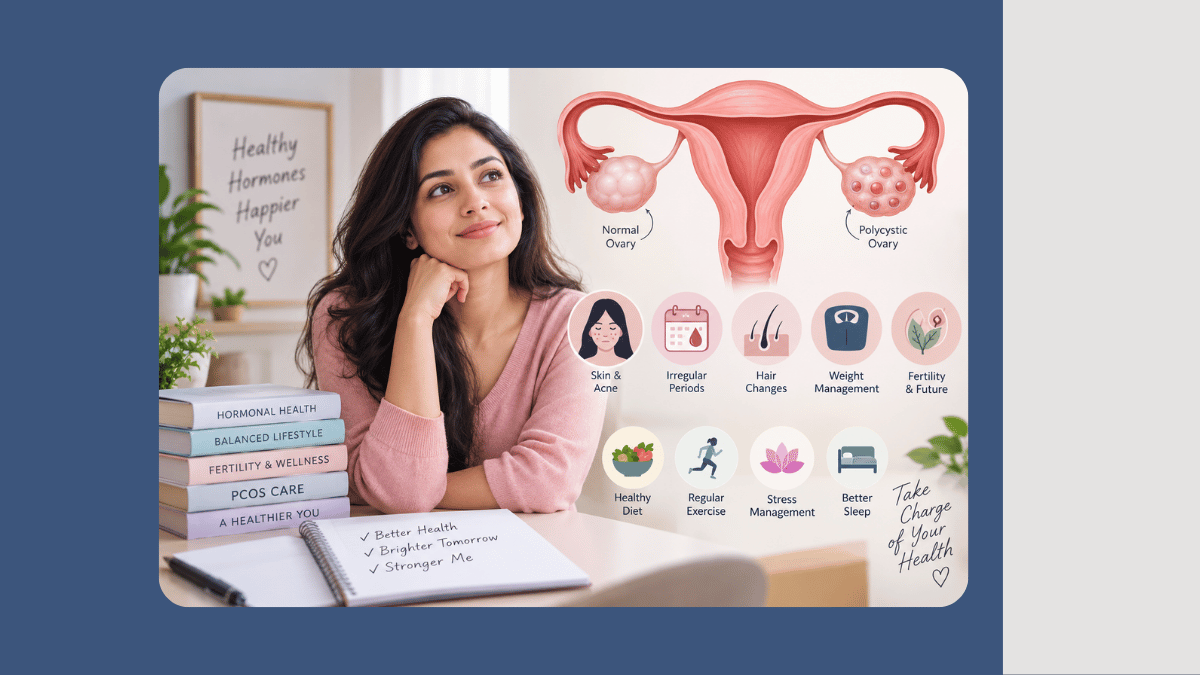
Polycystic ovary syndrome, or PCOS, is the most common hormonal disorder in women of reproductive age, affecting an estimated one in ten women in India and up to one in five in some studies. In my gynaecology practice in Thrissur, it is the condition I encounter most frequently across all three of the clinics where I consult. PCOS is a genuine metabolic and hormonal disorder with real long-term consequences, but it is also one of the most manageable conditions in women's health when it is properly diagnosed, understood, and addressed with the right personalised treatment plan. I am Dr. Viji Praveen, Senior Consultant Gynaecologist and Infertility Specialist at Westfort Hospital, Raji Multispeciality Hospital, and Macare Valapad in Thrissur, with an MS in Obstetrics and Gynaecology from Grant Medical College and Sir JJ Group of Hospitals, Mumbai, and 13 years of clinical experience including my time at Birla Fertility and IVF. PCOS is not a barrier to pregnancy, a life sentence of irregular periods, or a condition that requires invasive treatment in most women, and this guide explains what it actually involves.
What Is PCOS and What Causes It?
PCOS, or polycystic ovary syndrome, is a hormonal and metabolic disorder characterised by three core features: irregular or infrequent ovulation, elevated androgen levels (male hormones, of which testosterone is the most recognised), and the appearance of multiple small follicles in the ovaries on ultrasound. The Rotterdam Criteria, which are the most widely used diagnostic framework, require two of these three features to be present for a PCOS diagnosis. This means that not every woman diagnosed with PCOS has all three features, and two women carrying the same diagnosis can have quite different clinical presentations. The name polycystic ovary syndrome is itself slightly misleading: the ovaries do not actually contain cysts in the medical sense of the word. What the ultrasound shows are multiple immature follicles, small fluid-filled structures that would normally develop into dominant follicles capable of releasing an egg, but that in PCOS fail to progress normally, resulting in a characteristic appearance sometimes described as a string of pearls. The fundamental mechanism in PCOS is insulin resistance in a significant proportion of women with the condition, which drives elevated insulin levels that in turn stimulate the ovaries to produce excess androgens, disrupt normal follicle development, and suppress regular ovulation.
How Does PCOS Present? Symptoms to Recognise
The symptoms of PCOS vary considerably between women, and one of the most common clinical challenges is that women seek help for what they believe are separate and unrelated problems, not realising that they are all expressions of the same underlying condition.
Menstrual Irregularity
Irregular periods are the most common presenting complaint among women with PCOS in Kerala. Cycles that are longer than 35 days, that come unpredictably at intervals of weeks to months, or that are absent for extended periods (oligomenorrhoea and amenorrhoea) reflect the infrequent and irregular ovulation that is central to PCOS. In the Kerala context, I have observed that irregular periods are often normalised within families, particularly if a mother or older female relatives have had similar patterns, and women sometimes present only when they are trying to conceive and realise that their irregular cycles are making conception unlikely. Any woman whose periods are consistently more than 35 days apart, or who has fewer than eight periods per year, warrants a gynaecological evaluation regardless of whether she is currently planning pregnancy.
Androgen-Related Features
Elevated androgens in women with PCOS can manifest as unwanted facial or body hair (hirsutism), acne that persists beyond adolescence or is disproportionately severe, and in some women, scalp hair thinning or hair loss in a male pattern (androgenic alopecia). In my clinical observation, the presentation of androgen excess in Kerala and South Indian women tends to differ somewhat from what is described in Western literature, where hirsutism is often cited as a common presentation. South Indian women, including many patients I see in Thrissur, more frequently present with acne and irregular periods as the dominant features, with hirsutism being less clinically prominent. This does not mean androgen excess is absent; it is important to measure serum androgens rather than relying on clinical features alone.
Weight and Metabolic Features
Approximately 50 to 70 percent of women with PCOS have insulin resistance, and many (though not all) have excess weight, particularly around the abdomen. Insulin resistance in PCOS contributes to a significantly increased long-term risk of type 2 diabetes, gestational diabetes in pregnancy, and cardiovascular disease if it is not addressed. Weight management is therefore not simply an aesthetic concern in PCOS; it is a metabolic health imperative with long-term implications for cardiovascular and reproductive wellbeing.
How Is PCOS Diagnosed?
PCOS is a clinical diagnosis supported by blood tests and pelvic ultrasound, and it requires the exclusion of other conditions that can mimic its features, particularly thyroid disease, hyperprolactinaemia, congenital adrenal hyperplasia, and androgen-secreting tumours. The blood tests I routinely order in a PCOS evaluation include LH (luteinising hormone) and FSH (follicle stimulating hormone) and the LH/FSH ratio, total and free testosterone, DHEAS, a thyroid profile (TSH and free T4), prolactin, fasting insulin and glucose, an HbA1c to assess long-term glucose regulation, and a fasting lipid profile to assess cardiovascular risk. The pelvic ultrasound, ideally transvaginal for the most accurate follicle count, provides the ovarian morphology component of the Rotterdam Criteria. A thorough PCOS evaluation investigates the hormonal, metabolic, and ovarian dimensions of the condition together rather than treating the irregular periods in isolation from the metabolic risk.
PCOS and Fertility: What Every Woman Planning Pregnancy Needs to Know
PCOS is the single most common cause of anovulatory infertility, meaning infertility caused by the absence of regular ovulation rather than by blocked tubes, sperm problems, or structural uterine abnormalities. This distinction is clinically important, because anovulatory infertility is generally among the most treatable categories of infertility. The vast majority of women with PCOS who want to conceive will do so, often without requiring IVF. The treatment pathway is stepped: lifestyle intervention comes first, ovulation induction medications come second, and IUI and IVF are options for women who do not respond to or conceive with earlier steps. IVF is not the first treatment for PCOS-related infertility.
Lifestyle Intervention: The Most Underestimated Treatment
In overweight women with PCOS, a weight reduction of as little as five to ten percent of body weight can restore regular ovulation and spontaneous menstrual cycles. This is one of the most clinically impactful interventions available and one that requires no prescription. The mechanism is straightforward: weight loss reduces insulin resistance, which lowers circulating insulin, which reduces ovarian androgen production, which allows normal follicle development and ovulation to resume. The dietary approach that has the most evidence in PCOS combines reduction of refined carbohydrates, which drive insulin spikes, with regular moderate aerobic exercise. I always address this in detail at the first consultation, because results from lifestyle changes can be seen within three to four months.
Ovulation Induction
When ovulation induction is indicated, the first-line pharmacological treatment is letrozole, an aromatase inhibitor that has superseded clomiphene citrate as the preferred option in PCOS-related anovulatory infertility based on evidence showing better ovulation and live birth rates. Letrozole is taken for five days in the early part of the cycle, with an ultrasound monitoring scan to confirm follicle development and guide the timing of intercourse or IUI. The response to letrozole in PCOS is generally good, and many women conceive within three to six monitored cycles.
IUI and IVF in PCOS
Intrauterine insemination (IUI) is considered when ovulation induction with timed intercourse has not resulted in conception, when there are mild sperm concerns alongside the ovulation disorder, or as a more controlled intervention than timed intercourse. IVF is reserved for women who do not respond to ovulation induction, whose tubes are blocked, or whose partners have a significant sperm factor. In my experience at Birla Fertility and IVF in Thrissur, the IVF outcomes in women with PCOS are generally good, but the approach to stimulation requires particular care: women with PCOS are at higher risk of ovarian hyperstimulation syndrome (OHSS), a potentially serious complication of ovarian stimulation, and the stimulation protocol must be designed to reduce this risk while achieving an adequate response. Careful, personalised IVF stimulation planning in PCOS significantly reduces the risk of hyperstimulation while optimising egg yield.
Managing PCOS When Pregnancy Is Not the Goal
Not every woman with PCOS is trying to conceive. Many are seeking help for irregular periods, acne, hair concerns, or simply wanting to understand what PCOS means for their long-term health. The management goals in this group are different, and they deserve a treatment plan that addresses what actually matters to them.
Regulating the Menstrual Cycle
Infrequent or absent periods in women who are not trying to conceive create a risk that is less commonly understood: without regular shedding, the uterine lining (endometrium) can become excessively thickened (endometrial hyperplasia) over time, increasing the long-term risk of endometrial cancer. Women with PCOS who have fewer than four periods per year should have their endometrium protected, either through the use of combined oral contraceptives, which regulate the cycle while also addressing androgen-related features like acne and hirsutism, or through cyclical progestin to induce regular withdrawal bleeds. Regular endometrial protection in women with infrequent periods is a long-term cancer risk reduction strategy.
Managing Acne and Hirsutism
Androgen-related features like acne and unwanted hair are often the presenting concern for younger women with PCOS, and they can have a significant impact on self-esteem and quality of life. Combined oral contraceptives reduce androgen production and binding, improving both acne and hirsutism over a period of months. Anti-androgen medications can be added for more severe cases. It is important for patients to understand that these treatments improve the symptoms of androgen excess without treating the underlying PCOS, and that the symptoms may return when treatment is stopped.
PCOS and Long-Term Health: What to Monitor Over the Years
PCOS is a lifelong condition. The ovarian and hormonal features may become less prominent after menopause, but the metabolic consequences persist. Women with PCOS have a significantly higher lifetime risk of type 2 diabetes, gestational diabetes, hypertension, dyslipidaemia, and non-alcoholic fatty liver disease compared with women without PCOS. These risks are amplified by obesity and insulin resistance, and they are the reason why PCOS management should never be limited to the reproductive years. I recommend that women with PCOS have an annual fasting blood glucose and HbA1c check, a lipid profile, and blood pressure monitoring as a routine part of their preventive healthcare from the time of diagnosis onwards. PCOS is a metabolic condition that requires lifelong attention, not just management during the years of trying to conceive.
When to Consult a Gynaecologist About PCOS
A gynaecological evaluation is appropriate for any woman who has irregular or infrequent periods, is struggling with acne or unwanted hair that does not respond to standard treatment, is finding it difficult to lose weight despite genuine effort, has been told she may have PCOS but has never had a full evaluation, or is planning to conceive and wants to understand how PCOS may affect her fertility. An evaluation is also appropriate for women who have been diagnosed but whose management consists only of a prescription for the pill without any explanation of the underlying condition, the metabolic risks, or the plan for when they decide to conceive. In Thrissur, I see patients at Westfort Hospital, Raji Multispeciality Hospital, and Macare Valapad across the week, and I approach every PCOS consultation with the same philosophy: the treatment plan has to be built around what matters most to this particular woman at this point in her life, whether that is getting pregnant, managing her periods, clearing her skin, or protecting her long-term metabolic health. A personalised PCOS consultation at Westfort Hospital or Raji Multispeciality Hospital, Thrissur is the starting point for understanding your specific condition and building the right plan.
To book a consultation with Dr. Viji Praveen at Westfort Hospital, Thrissur (Tuesday, Thursday, Saturday, 9:30 AM to 12:30 PM, call 0487 2439333), or Raji Multispeciality Hospital, Thrissur (Monday, Friday, 9:30 AM to 12:30 PM, call +91 6238756018), or Macare Valapad (Wednesday, 11 AM to 2 PM, call +91 8943920068).
Written by Dr. Viji Praveen, MBBS (Seth GS Medical College and KEM Hospital, Mumbai), MS Obstetrics and Gynaecology (Grant Medical College and Sir JJ Group of Hospitals, Mumbai University), Senior Consultant Gynaecologist and Infertility Specialist, Westfort Hospital, Thrissur (Tuesday, Thursday, Saturday, 9:30 AM to 12:30 PM), Raji Multispeciality Hospital, Thrissur (Monday, Friday, 9:30 AM to 12:30 PM), Macare Valapad (Wednesday, 11 AM to 2 PM). 13+ years. 10,000+ patients. Phone: +91 8606496008.
Related reading
Are Irregular Periods Affecting Your Chances of Pregnancy?
We've Been Trying for a Baby. When Should We Seek Fertility Help?
Infertility Evaluation and Assisted Reproductive Treatment
Menstrual Disorders and Hormonal Imbalances


Add a Comment